

Table of Contents
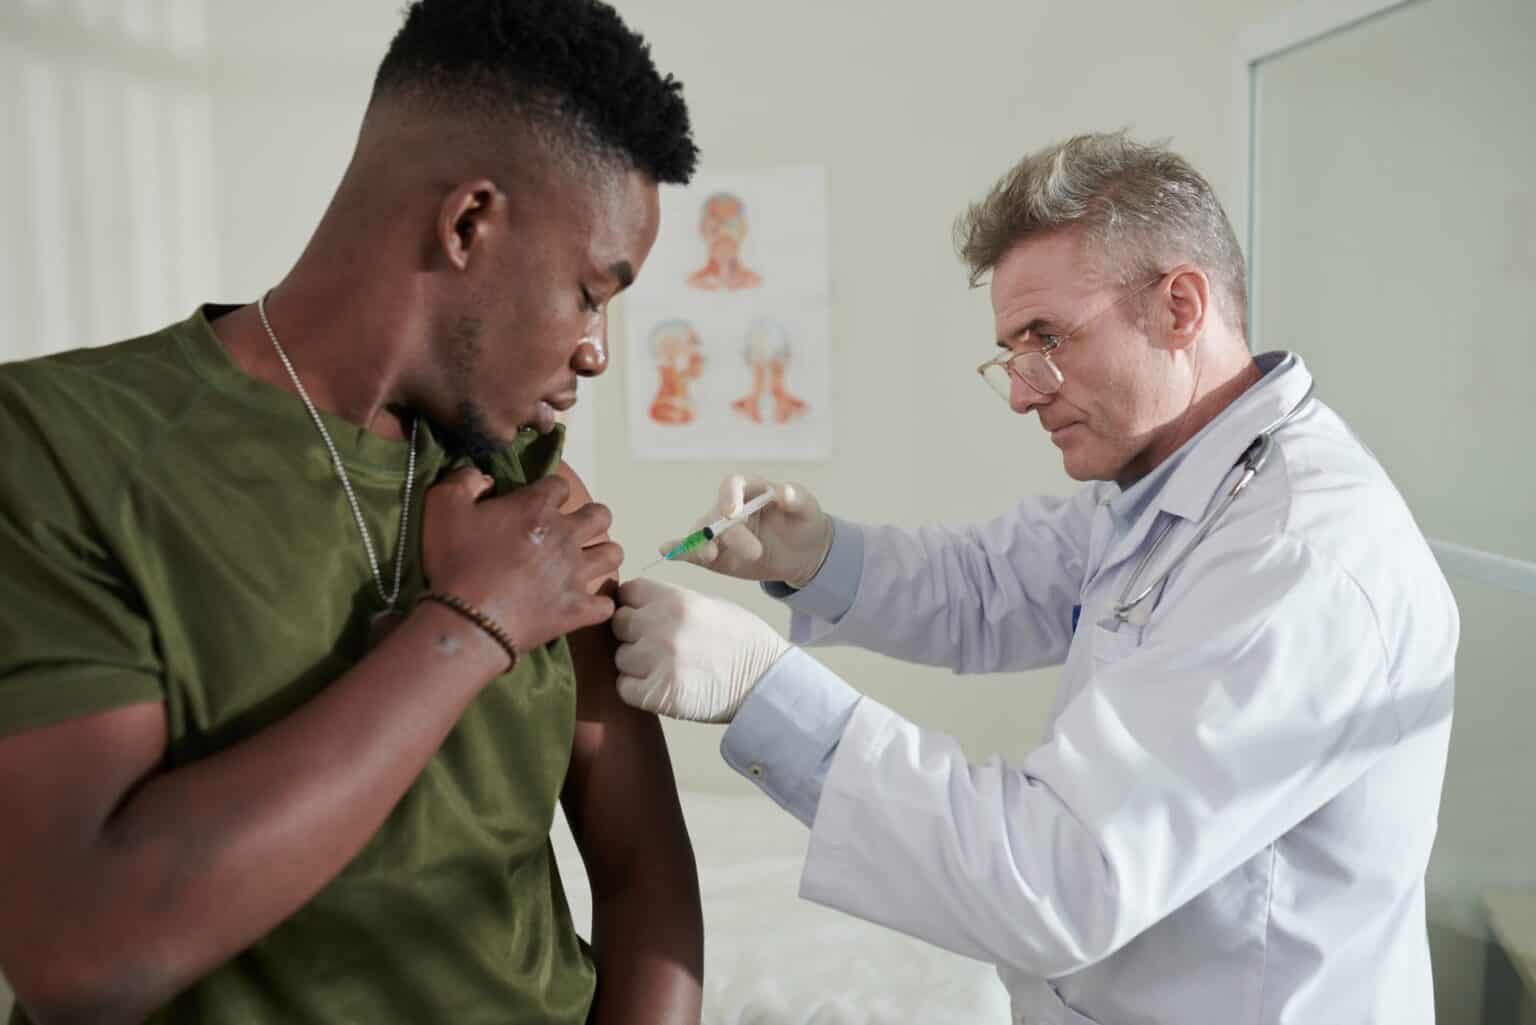
The peanut butter shot is an injection of benzathine penicillin G, sold as Bicillin L-A, given deep into the buttock muscle of new recruits in their first days of training. It is an antibiotic, not a vaccine. One dose keeps penicillin in the blood for weeks and protects a crowded barracks against group A strep, the bacterium behind strep throat and rheumatic fever.
It is still given, but not everywhere. In the most recent published review of every training center, the Navy, the Marine Corps, the Air Force and two Army posts gave it to every incoming recruit. The Coast Guard and two other Army posts did not.
The name is also used for a bar shot made with peanut butter whiskey. This article is about the injection.
| Question | Answer |
|---|---|
| What it is | Benzathine penicillin G (Bicillin L-A), a long-acting antibiotic |
| Recruit dose | 1.2 million units in a 2 mL prefilled syringe |
| Where it goes | Deep into the upper, outer buttock or the side of the hip |
| What it prevents | Group A strep: strep throat, strep pneumonia, rheumatic fever |
| How long it lasts | Blood levels for about 14 days, traces for 4 weeks |
| If you are allergic | Weekly oral azithromycin or erythromycin instead |
| Discontinued? | No, but the drug has been in national shortage since April 2023 |
What Is the Peanut Butter Shot?
The drug is penicillin G bound to a second molecule, benzathine, which makes it very slightly soluble in water. Instead of dissolving, it is shipped as a suspension of tiny crystals that the label describes as “viscous and opaque.”
That is the whole trick. Injected into a large muscle, the crystals form a depot that releases penicillin slowly, so a single shot does the work of weeks of pills that a recruit might forget to take.
The label for Bicillin L-A allows only one route: deep intramuscular injection into the upper, outer quadrant of the buttock or the ventrogluteal site on the side of the hip. The syringe label carries “WARNING: FATAL IF GIVEN BY OTHER ROUTES,” because an accidental injection into a vein can cause cardiac arrest.
Myth: It is a vaccine that kills everything
Popular write-ups call it a vaccination and say it wipes out a variety of bacteria in one go. It is neither. It is an antibiotic, and the military gives it to recruits for one target: group A streptococcus. The vaccines recruits receive in processing are separate shots in the arm.
Why Is It Called the Peanut Butter Shot?
Because of how it looks and moves. The suspension is thick, pale and opaque, and it has to be pushed through the needle slowly. Like a lot of military slang, the nickname stuck because every recruit understands it on the first try.
There is no peanut in it. The label lists the inactive ingredients as sodium citrate, povidone, carboxymethylcellulose sodium, lecithin and two parabens, all in a water base.
The first version really did use peanut oil
When military researchers began testing long-acting penicillin on airmen at Warren Air Force Base in January 1949, the drug they injected was procaine penicillin G suspended in peanut oil with 2% aluminum monostearate. Today’s Bicillin L-A is water-based. The nickname describes its texture, not its history, but the coincidence is real.
Why Do Military Recruits Get the Peanut Butter Shot?
Basic training packs thousands of young adults from every corner of the country into shared barracks, then wears them down with exercise, stress and short sleep. Group A strep spreads well in exactly those conditions.
The danger is less the sore throat than what can follow it. Untreated strep can trigger acute rheumatic fever, which can scar the heart valves for life, and kidney inflammation called glomerulonephritis. In the Second World War the Army, which then included the Army Air Forces, recorded 18,339 hospital admissions for acute rheumatic fever between 1942 and 1945.
A single 1.2 million-unit dose keeps penicillin in the blood for about 14 days and leaves detectable traces for four weeks, according to the label. That covers the early weeks of training, when a new cohort is mixing germs for the first time.
It also appears to cut sickness in general. A 2018 analysis of 26 years of weekly respiratory illness data from recruit camps found that periods with the shot in use had a 32% lower rate of acute respiratory disease, though the adenovirus vaccine mattered more.

The Air Force Base Where the Shot Proved Itself
Much of the evidence behind the peanut butter shot was built on airmen. In 1943 large numbers of rheumatic fever cases were reported from Lowry Field and Buckley Field, two Army Air Forces training bases in Colorado, and from Fort Francis E. Warren in Wyoming.
In January 1949 the Armed Forces Epidemiological Board opened a Streptococcal Disease Laboratory in a converted wooden hospital ward at Warren, soon renamed Warren Air Force Base. The base sits outside Cheyenne at just over 6,000 feet (1,830 m), where minus 20°F (minus 29°C) was common in winter. It housed an Air Force technical training wing and had one of the highest strep and rheumatic fever rates the researchers could find.
The first trial was blunt. Airmen hospitalized with strep throat were split by serial number: 798 with even numbers got penicillin and 804 with odd numbers served as controls. Rheumatic fever developed in 2 of the treated men and 17 of the untreated ones.
By 1953 the lab was testing benzathine penicillin, the drug in today’s shot. A single injection given to 2,214 airmen during a strep epidemic brought a prompt drop in infections. A dose comparison found that 1.2 million units protected for 6 to 7 weeks, 600,000 units for 4 to 5 weeks and 300,000 units for only 1 to 2 weeks.
That is why recruits still get 1.2 million units. In October 1953 a committee chaired by the lab’s director, Dr. Charles Rammelkamp, recommended 1.2 million units of benzathine penicillin, or a 10-day course of oral penicillin, whenever strep was epidemic in the armed forces.
The Navy and Marine Corps began using benzathine penicillin in their recruit camps the same year. The Warren lab won the Albert Lasker Group Award in 1954 and closed in September 1955.
Which Branches Still Give the Peanut Butter Shot?
There is no single military-wide rule. Military policy says routine penicillin for basic trainees “should be directed by [the] local preventive medicine authority,” so each training center decides for itself based on its own strep history.
The most recent public site-by-site picture comes from a 2019 review led by an epidemiologist at the U.S. Air Force School of Aerospace Medicine, which tracked every basic training center through 2017.
| Training center | Branch | Routine peanut butter shot | Extra doses |
|---|---|---|---|
| Recruit Training Command Great Lakes, Illinois | Navy | Yes, year-round | Second dose October to March |
| MCRD San Diego, California | Marine Corps | Yes, year-round | Second and third doses year-round |
| MCRD Parris Island, South Carolina | Marine Corps | Yes, year-round | Second dose in peak season |
| JBSA-Lackland, Texas | Air Force | Yes, year-round | None |
| Fort Leonard Wood, Missouri | Army | Yes, year-round | None |
| Fort Sill, Oklahoma | Army | Yes, year-round | None |
| Fort Benning, Georgia | Army | Stopped in 2016 | Surveillance only |
| Fort Jackson, South Carolina | Army | No, 2008 to 2017 | Surveillance only |
| Training Center Cape May, New Jersey | Coast Guard | No | Surveillance only |
So the answer to “does the Army do the peanut butter shot” is that it depends on the post. The review notes that Army policy “varies widely” among its training centers, while Air Force basic training gives it to everyone at a single site.
That site is Lackland, part of Joint Base San Antonio. A 2024 case report from Brooke Army Medical Center, also in San Antonio, describes a recruit who received the injection “as part of standard prophylaxis” during basic military training, so the practice was still routine well after the review.
The policy covers all incoming recruits at the centers that use it, so women receive it the same as men. The Navy goes furthest, adding a second dose halfway through boot camp at Great Lakes during the winter strep season.
Why Does the Peanut Butter Shot Hurt So Much?
It is a large volume of thick liquid going deep into a muscle. The 1.2 million-unit syringe holds about 2 mL, and the label warns that the needle “may be blocked if the injection is not made at a slow, steady rate,” so the push takes a while.
Then the drug stays put. The depot that makes the shot effective is the same lump that makes sitting down miserable for a few days. The 2019 review notes that most training centers postpone physical training until the day after the injection.
Myth: It uses a 12-gauge needle
The Marine Corps comic Terminal Lance joked about a 12-gauge needle, and the number gets repeated as fact. Pfizer’s 1.2 million-unit Bicillin L-A syringe ships with a 21-gauge, 1.5-inch needle. Gauge numbers run backwards, so a 12-gauge needle would be far thicker. The pain comes from the thick drug, not a giant needle.
Serious reactions are rare. In the early Navy trials, 0.98% of 32,419 recruits had an allergic reaction, mostly hives, joint pain and fever, and none had anaphylaxis. The 2019 review’s authors knew of no anaphylaxis at a training center since active surveillance began in 1998.
Unusual injuries do happen. The 2024 San Antonio case involved a 25-year-old recruit whose gluteal muscle became inflamed after the shot. He was admitted to the hospital and recovered fully within about two weeks.
What If You Are Allergic to Penicillin?
You skip the injection, not the protection. At centers that use the shot, recruits with a penicillin allergy are prescribed weekly oral azithromycin or erythromycin, which recruits call the “peanut butter pills.”
The military learned this the hard way. A study of 736 Marine Corps recruits in early 1989 found that the 7% who were allergic and got no antibiotic were more likely to carry strep, and platoons with more of them had more infections among everyone else.
Once the allergic recruits were put on oral erythromycin, the weekly rate of strep throat fell by more than 75%. A recruit who skips protection becomes a reservoir for the whole platoon.
Many allergy labels are wrong, too. Fewer than 20% of people who report a penicillin allergy test positive on skin testing, but confirming that for every recruit is impractical, so self-reported allergies are simply accepted.
What Happens When the Military Stops Giving It
This is the strongest argument for the shot. Several times since the 1970s, a training center decided strep was no longer a threat and stopped the injections. The record of what followed is consistent.
Mid-1970s
Air Force basic training stops universal prophylaxis. It is reinstated at Lackland in January 1989 after a three-week outbreak of 186 cases of strep throat among trainees.
1980
Naval Training Center San Diego ends its program. Over eight months from December 1986, 10 recruits develop rheumatic fever and 6 get strep pneumonia. The shots resume and the outbreak stops.
1988
Fort Leonard Wood restarts the shot. Army training centers had dropped it in the early 1980s. A five-month outbreak brings 22 throat abscesses and 13 cases of rheumatic fever before it resumes.
1989 and 1993
Fort Leonard Wood stops again, twice. Both times, strep rates rise within two months.
2002
The largest strep pneumonia outbreak in over 30 years. At a Marine Corps training camp, 127 Marines get pneumonia in seven weeks. Extra doses end it, and the gap between shots is cut from 28 to 35 days down to 21.
2003 to 2006
Invasive outbreaks at Fort Knox and Fort Leonard Wood. All three begin without routine prophylaxis. Cases include necrotizing fasciitis and toxic shock, and one death.
The 2019 review’s conclusion was plain: training center authorities “should be extremely cautious about discontinuing benzathine penicillin chemoprophylaxis.”
Is the Peanut Butter Shot Discontinued?
No. What people are noticing is a shortage. The FDA listed Bicillin L-A as in shortage on April 26, 2023, and Pfizer is the only supplier of Bicillin L-A.
It has not recovered. In July 2025 Pfizer’s subsidiary King Pharmaceuticals recalled specific lots after particles were found during inspection. San Francisco’s health department now projects the shortage to last through the fourth quarter of 2027.
Civilian health officials are prioritizing it for syphilis in pregnancy, where long-acting penicillin is the only recommended treatment. San Francisco is asking doctors to use penicillin V, amoxicillin or azithromycin for strep throat instead.
The military has handled shortages before. During shortages in 2005 and 2006, Fort Leonard Wood kept its limited supply for affected units and gave oral penicillin to everyone else, and in 2017 Lackland used the shot or azithromycin depending on stock.
We found no public Department of Defense statement on how the current shortage has changed practice at each center. A recruit shipping out in 2026 should expect either the shot or the pills, depending on supply at their training site.
FAQ
Sources and references used for research and fact-checking.
- Defense Technical Information Center, Chemoprophylaxis against group A streptococcus during military training (Preventive Medicine, 2019)
- AMEDD Center of History and Heritage, History of the Commission on Streptococcal and Staphylococcal Diseases
- DailyMed, U.S. National Library of Medicine, Bicillin L-A (penicillin G benzathine injectable suspension) prescribing information
- Reviews of Infectious Diseases (PubMed), Penicillin prophylaxis for streptococcal infections in United States Navy and Marine Corps recruit camps, 1951-1985
- New England Journal of Medicine (PubMed), Hyperendemic Streptococcus pyogenes infection despite prophylaxis with penicillin G benzathine
- Clinical Infectious Diseases (PubMed), Pneumonia outbreak associated with group A Streptococcus species at a military training facility
- Epidemiology and Infection (PubMed), The role of benzathine penicillin G in predicting and preventing all-cause acute respiratory disease in military recruits: 1991-2017
- American Journal of Case Reports (PubMed), A 25-year-old military recruit with isolated myositis following routine chemoprophylaxis with intramuscular benzathine penicillin G
- Virginia Department of Health, Shortage of Penicillin G Benzathine (Bicillin L-A)
- County of San Luis Obispo Public Health Department, Bicillin L-A Recall and National Shortage
- San Francisco Department of Public Health, Penicillin G Benzathine (Bicillin L-A) Shortage Continues Through 4th Quarter of 2027
- We Are The Mighty via Yahoo News, Why the 'peanut butter' shot is the most dreaded injection
- Terminal Lance, The Peanut Butter Shot
Get the Newsletter
The latest aviation news and stories sent to your inbox.
About the Author

Tim is the owner and lead editor of AeroCorner since 2019, overseeing aviation content covering aircraft, airlines, airports, and the broader aviation industry. Through years of researching, writing, editing, and publishing aviation-focused content, he has developed extensive practical knowledge of commercial aviation and air travel. Based in Asia and a frequent traveler himself, Tim also brings firsthand passenger experience to AeroCorner’s coverage. Outside of publishing, he has also explored aviation firsthand through hands-on flight training in New Zealand.